
General Information
Rhinoplasty vs. Septoplasty vs. Septorhinoplasty: What's the Difference?
Nose Journey
NoseJourney Expert
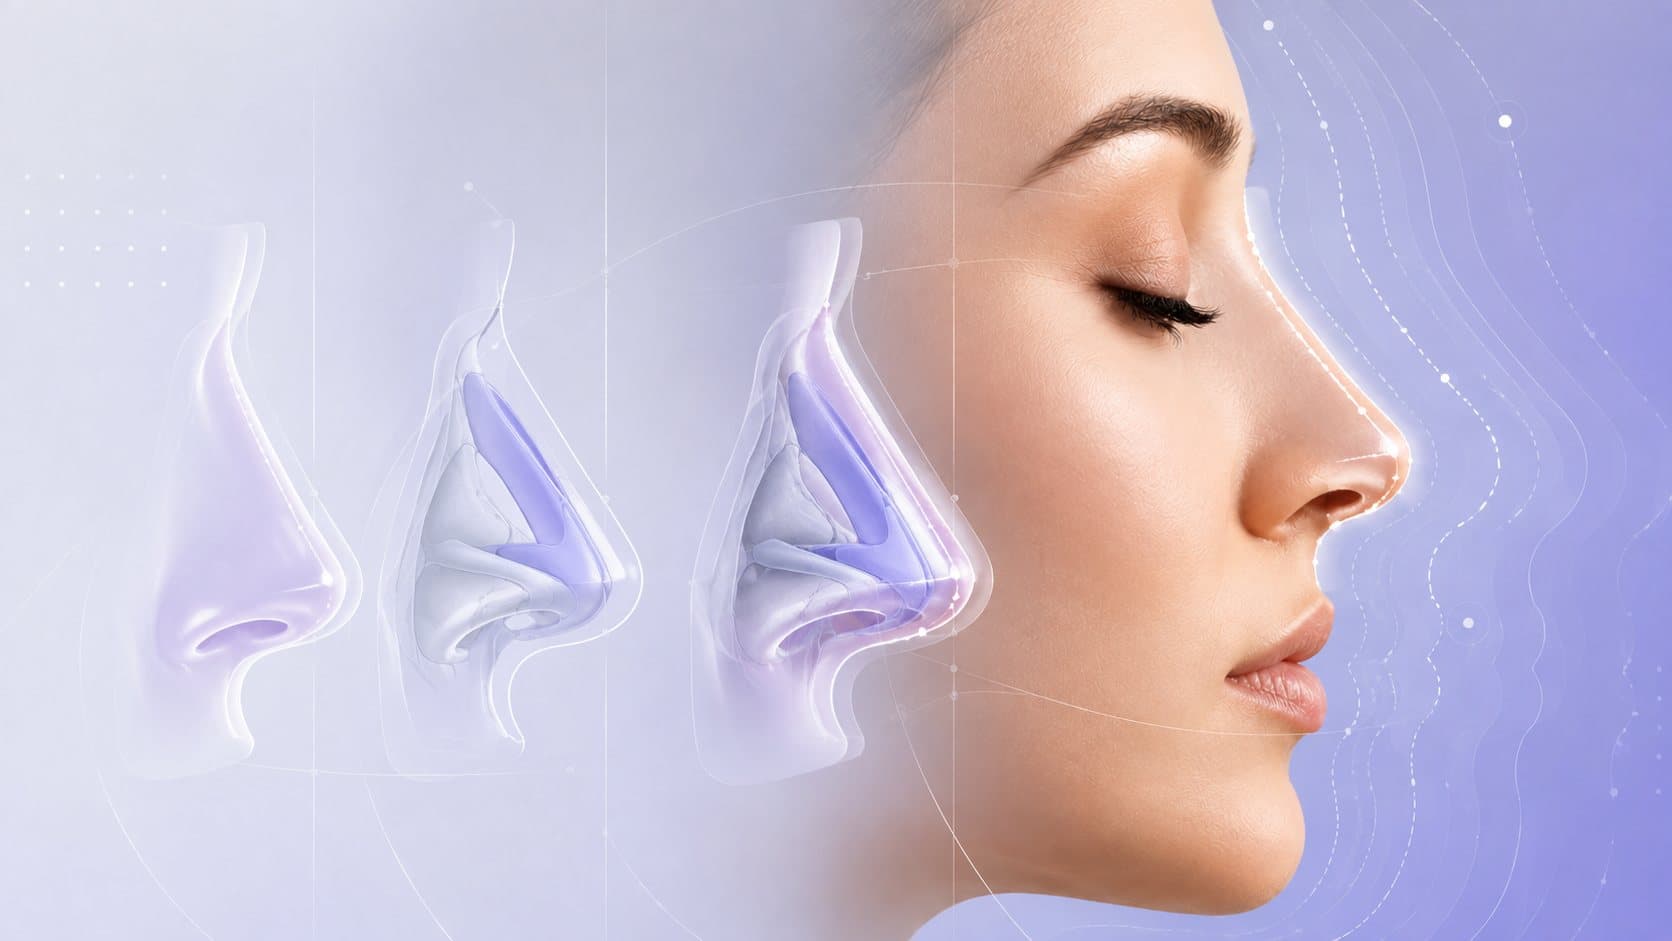
A clear guide to the differences between rhinoplasty, septoplasty, and septorhinoplasty, including how appearance goals, breathing concerns, and internal nasal structure can determine which term applies.
Rhinoplasty, septoplasty, and septorhinoplasty are often used interchangeably online, but they describe different primary goals. Rhinoplasty changes the external nose, septoplasty addresses the internal septum, and septorhinoplasty combines external and internal work in one plan. The terms are useful for understanding a recommendation, but symptoms and examination determine which procedure, if any, applies.
The basic distinction
Septoplasty addresses the septum, the internal wall of cartilage and bone separating the two nostrils, with the primary goal of improving airflow when a deviation causes nasal obstruction. It's a functional procedure first. Rhinoplasty addresses the external shape of the nose, primarily an aesthetic procedure, though it can incorporate functional elements when relevant. Septorhinoplasty combines both goals in a single operation.
The distinction is useful, but it isn't a hard wall: rhinoplasty planning frequently accounts for airflow even when the primary goal is appearance, and septoplasty can occasionally influence how the nose looks externally, depending on the specific anatomy and technique, even though that isn't its main purpose.
Use the terms to understand the plan, not to self-select surgery
A patient may arrive asking for septoplasty because one side feels blocked, or for rhinoplasty because the bridge looks crooked. Either concern can involve more than one structure. Describe what you see, what you feel, when the problem occurs, and whether injury or previous surgery is relevant. The surgeon can then explain which term matches the work needed, rather than forcing the symptoms into a procedure name chosen before examination.
How a deviated septum is typically identified
Evaluation often starts with your reported symptoms and a physical exam, sometimes including a basic internal look using a nasal speculum. Some surgeons use nasal endoscopy, a thin, lit scope, for a more complete internal view when needed. Imaging like a CT scan isn't something every case requires; it tends to come up when the clinical picture isn't clear from examination alone, or when more detailed surgical mapping is useful. It helps to know that a meaningful septal deviation can go unnoticed for years, since symptoms vary in severity and aren't always obvious day to day.
Why the two are sometimes combined
Trauma, prior injury, or natural asymmetry can affect the internal septum and the external shape of the nose at the same time. When a surgeon identifies both a cosmetic goal and a functional issue during evaluation, addressing them together in one septorhinoplasty is a common approach, often meaning one recovery period and one exposure to anesthesia, rather than two separate surgeries months apart. There's also a practical efficiency to it: when suitable, septal cartilage removed to straighten a deviation may sometimes be reused as grafting material for the cosmetic portion of the same surgery, rather than discarded and later needing to be sourced elsewhere.
Recovery differences between the three
As a general pattern, septoplasty alone tends to involve less visible swelling and bruising than procedures involving external reshaping, although internal congestion and discomfort can still occur during recovery. Rhinoplasty alone typically involves a longer period of visible swelling and bruising as the external work settles. Septorhinoplasty tends to follow a recovery pattern closer to rhinoplasty alone in terms of what's visible from the outside, though the combined internal and external work means individual experiences vary more than with either procedure in isolation.
A frequent misunderstanding worth clearing up
Some people assume septoplasty will change how the nose looks, or that rhinoplasty will resolve breathing problems as a side effect. Neither assumption holds up reliably. A surgical plan built purely around external appearance, without evaluating internal structure, can occasionally leave a functional issue untouched. External reshaping can affect airflow if internal function is not considered during planning. This is one of the reasons a full evaluation matters more than arriving at a consultation with a fixed procedure name already decided.
Insurance and coverage
Coverage rules differ substantially by country, insurer, and how well a functional issue is documented. In some places, a septoplasty addressing a diagnosed breathing impairment may be eligible for partial coverage; a purely cosmetic procedure often isn't. This varies enough that it's worth a direct conversation with your own insurer or the clinic's billing team rather than assuming a general rule applies.
Which term actually applies to you
This isn't something you can determine from a mirror or a list of symptoms alone. Chronic congestion, a visibly crooked bridge, snoring, or a history of nasal injury are all reasons a surgeon might recommend a combined approach, but final confirmation often requires a proper clinical assessment, often including an in-person internal examination of both your internal and external anatomy.
Three questions before choosing a procedure name
Start with the concern rather than the label.
What do you want to change externally?
What breathing or congestion symptoms do you experience?
What does the internal and external examination show?
The answers may point toward a cosmetic plan, a functional plan, a combined operation, or no operation at all. This order matters because a patient cannot reliably diagnose a septal deviation from appearance alone, and a visible change does not automatically resolve airflow. Procedure names are most useful after assessment, when they describe the work being proposed rather than serving as a self-selected solution.
Questions that clear up the procedure names
Will septoplasty change the way my nose looks?
Not reliably. Its primary purpose is to correct the septum and improve airflow, although external appearance can sometimes change depending on the anatomy and technique.
Will rhinoplasty fix breathing problems automatically?
No. Breathing problems need to be identified and included in the surgical plan. An operation designed only around appearance may leave a functional issue untreated.
Can septoplasty and rhinoplasty be performed together?
Yes. When both internal and external concerns are present, septorhinoplasty may address them during one operation and one recovery period.
Is recovery from septorhinoplasty the same as septoplasty alone?
It generally resembles rhinoplasty more closely in terms of visible swelling and bruising because the external nose is also healing.
How can I know whether I have a deviated septum?
Symptoms can raise the question, but confirmation requires an internal examination. A mirror, photograph, or symptom list alone cannot establish the diagnosis.
Is the functional part always covered by insurance?
Coverage varies by country, insurer, and documentation of medical necessity. The clinic and insurer need to confirm what applies to the individual plan.
Let the diagnosis define the procedure
The three names describe the intended work, not a diagnosis you can confirm from a mirror or symptom list. Use them to follow the surgeon's explanation, then make sure the plan addresses both external goals and internal function where relevant.
NoseJourney AI
Start Your Rhinoplasty Journey with AI
Answer a few questions and get matched instantly with verified specialist surgeons who specialize in your case.
Written by
Nose Journey
NoseJourney Expert
Expert contributor to the NoseJourney Knowledge Hub. Dedicated to providing accurate, evidence-based information about rhinoplasty procedures and recovery.
Your next chapter